

You’ve tried therapy. You’ve done the exposure exercises. But those intrusive thoughts still loop in your head like a broken record, and the compulsions feel impossible to resist. If you’re looking for pharmacological help, you are likely facing a confusing array of pill names, dose numbers, and conflicting advice. The good news? There are only two main classes of medications proven to work for Obsessive-Compulsive Disorder (OCD) as standalone treatments: Selective Serotonin Reuptake Inhibitors (SSRIs) and Clomipramine.
Here is the reality check most patients miss: OCD requires higher doses than depression, and it takes longer to work. A standard antidepressant dose often does nothing for OCD. You need patience, precise titration, and a clear understanding of what each drug actually does. This guide breaks down exactly how these medications work, what doses matter, and how to navigate the side effects without giving up too soon.
The Big Two: Why SSRIs and Clomipramine?
Why do we talk about just two types of drugs when there are dozens of psychiatric medications? Because science has been brutally selective here. According to the International OCD Foundation, SSRIs and Clomipramine are the only medications with robust evidence supporting their use as first-line or second-line monotherapies for OCD. Other drugs might help with anxiety or mood, but they don’t reliably stop the obsessive-compulsive cycle on their own.
SSRIs include familiar names like fluoxetine (Prozac), sertraline (Zoloft), paroxetine (Paxil), and fluvoxamine (Luvox). They work by blocking the reabsorption of serotonin in the brain, keeping more of this neurotransmitter available to regulate mood and anxiety. Because they have a cleaner safety profile, guidelines from the American Psychiatric Association recommend them as the starting point for almost everyone.
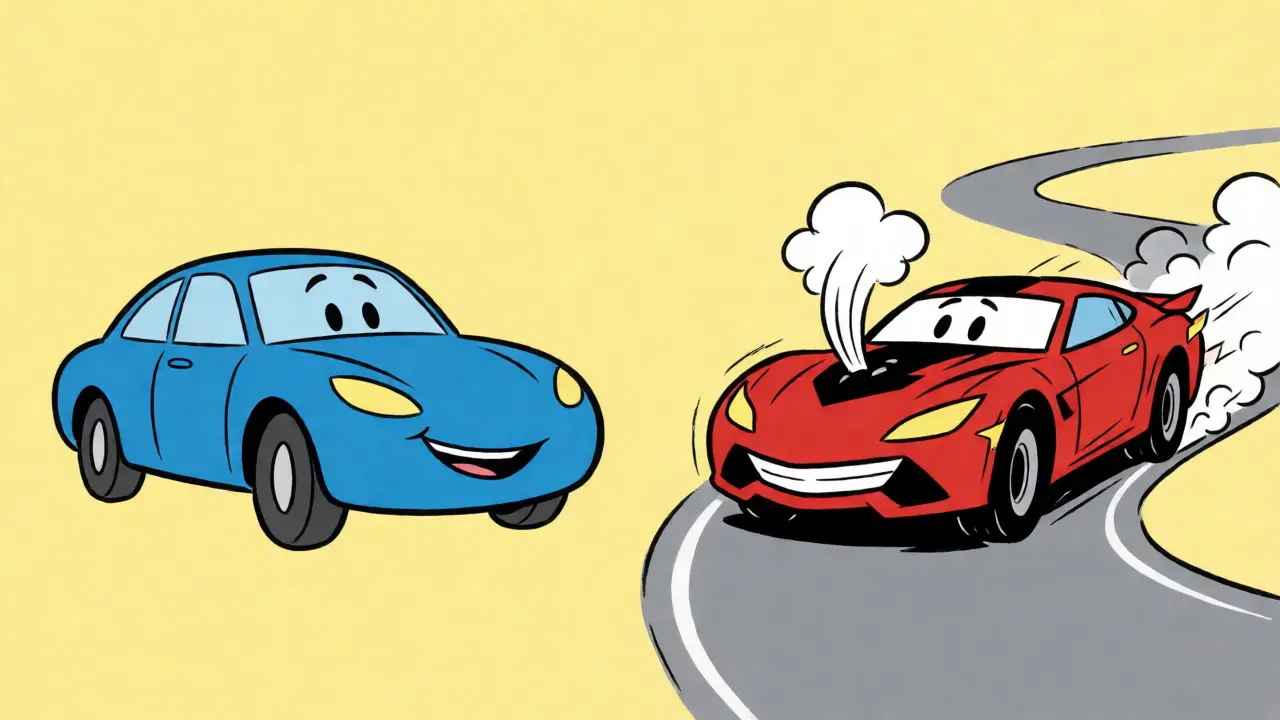
Clomipramine (Anafranil) is different. It’s a tricyclic antidepressant (TCA) that was actually the first drug FDA-approved specifically for OCD back in 1989. It works similarly to SSRIs but hits additional receptors, which can make it more potent for stubborn cases. However, that extra potency comes with a heavier side-effect burden. Think of SSRIs as the reliable sedan-safe, efficient, easy to drive. Clomipramine is the sports car-powerful, capable of going faster, but harder to handle and requiring more maintenance.
Dosing Realities: Higher Than You Expect
This is where most treatment plans fail. Patients start an SSRI at the dose used for depression, wait four weeks, see no change, and quit. For OCD, that approach is flawed. You typically need doses at the upper end of the approved range, and you need to stay on them long enough to see results.
An adequate trial means staying on a therapeutic dose for 8 to 12 weeks. Crucially, at least six of those weeks must be at a moderate-to-high dose. Low doses rarely touch OCD symptoms. Here is what "therapeutic" looks like in practice:
| Medication | Starting Dose | Target Therapeutic Range | Max Daily Dose |
|---|---|---|---|
| Sertraline | 25-50 mg | 200-300 mg | 300 mg* |
| Fluoxetine | 10-20 mg | 40-60 mg | 80 mg |
| Paroxetine | 10-20 mg | 40-60 mg | 60 mg |
| Fluvoxamine | 25-50 mg | 200-300 mg | 300 mg |
| Clomipramine | 25 mg | 100-250 mg | 250 mg |
*Note: While some guidelines cap sertraline at 200 mg, many OCD specialists push to 300 mg if tolerated, especially in severe cases.
Notice the gap between starting doses and target doses. With clomipramine, you might start at 25 mg and slowly increase by 25 mg every few days. It’s a slow climb because the body needs time to adjust to the anticholinergic effects (dry mouth, constipation, dizziness). Most adults won’t see significant relief until they hit at least 100 mg, and many need 150-250 mg. For children aged 10 and older, dosing is weight-based (1-3 mg/kg), but the ceiling remains around 200-250 mg.
Side Effects: The Trade-Offs
Let’s be honest about the downsides. SSRIs aren’t candy. Common issues include nausea, sexual dysfunction, sleep disturbances, and initial jitteriness. But these often fade after the first few weeks. Clomipramine is trickier. Its side effect profile is significantly harsher.
Patient forums and clinical data consistently highlight three major complaints with clomipramine:
- Anticholinergic effects: Dry mouth so severe you need water hourly, blurred vision, and constipation.
- Sedation: Many patients report feeling "foggy" or excessively tired, which is why doctors usually prescribe it at bedtime.
- Weight gain: Gaining 15-25 pounds within six months is a documented risk, particularly at doses above 100 mg.
There’s also a cardiovascular consideration. Clomipramine can prolong the QTc interval (a measure of heart rhythm), so regular ECGs are recommended once you exceed 150 mg/day. SSRIs generally don’t require this level of cardiac monitoring unless you have pre-existing heart conditions.
Despite these drawbacks, some patients find clomipramine superior for specific subtypes. Research suggests it may be particularly effective for contamination fears and cleaning rituals. If SSRIs haven’t touched your symptoms after two adequate trials, clomipramine isn’t a last resort-it’s a logical next step with distinct strengths.
How Long Until It Works?
Patience is non-negotiable. Unlike painkillers, these meds don’t offer instant relief. Here’s the typical timeline:
- Weeks 1-2: Side effects may appear before benefits. Anxiety might even spike temporarily. This is normal and usually passes.
- Weeks 4-6: Early signs of improvement. Sleep might improve, or the intensity of obsessions might drop slightly.
- Weeks 8-12: The critical window. If you’re at a therapeutic dose and haven’t seen at least a 25-35% reduction in symptoms (measured by scales like the Y-BOCS), the doctor will reassess.
- Months 3-6: Continued gradual improvement. Full benefit often takes up to six months.
A common mistake is stopping during week two because "it’s not working." Data from the NIMH shows that 37% of patients quit early due to initial discomfort, yet 89% of those who stuck it out saw resolution of those early side effects. Don’t let transient nausea rob you of long-term relief.

What If One Drug Doesn’t Work?
If the first SSRI fails, guidelines suggest trying a second one. Switching from fluoxetine to sertraline, for example, is common. Each drug interacts with serotonin transporters slightly differently. Some people respond better to one than another.
If two SSRIs fail, you have three main paths:
- Switch to Clomipramine: This is the classic move. Since clomipramine works via a broader mechanism, it can succeed where SSRIs failed. Studies show response rates of 40-60% in treatment-resistant cases when dosed correctly.
- Augmentation: Adding a low-dose antipsychotic (like risperidone or aripiprazole) to an SSRI. This is increasingly common and can boost response rates by 35-40% in partial responders.
- Combination Therapy: Using an SSRI plus low-dose clomipramine (25-75 mg). This leverages the efficacy of both while minimizing the high-dose side effects of clomipramine alone.
Remember, medication is rarely the whole solution. The gold standard for OCD treatment is combining medication with Exposure and Response Prevention (ERP) therapy. Pills lower the volume of the noise; ERP teaches you how to live with the quiet.
Frequently Asked Questions
Can I take OCD medication forever?
Not necessarily. Many patients taper off successfully after 1-2 years of stability, especially if combined with therapy. However, relapse rates are high if stopped too soon. Doctors usually recommend maintaining the lowest effective dose for at least 12 months after remission before attempting a slow taper.
Do SSRIs cause emotional numbness?
Some users report feeling "flat," but this is often dose-dependent. Lowering the dose slightly or switching to a different SSRI (like fluoxetine vs. paroxetine) can resolve this. It’s not inevitable, and adjusting the regimen usually fixes it.
Is clomipramine stronger than SSRIs?
In head-to-head adult trials, efficacy is often comparable. However, clomipramine tends to show higher response rates in pediatric populations and treatment-resistant adults. The trade-off is significantly higher side effects, which is why SSRIs remain first-line.
What if I miss a dose?
Take it as soon as you remember. If it’s close to your next dose, skip the missed one. Never double up. Consistency matters more than perfection, but frequent misses can trigger withdrawal-like symptoms, especially with short-half-life drugs like paroxetine.
Are there natural alternatives?
Supplements like N-acetylcysteine (NAC) or inositol have shown modest promise in small studies, but none match the robust evidence base of SSRIs or clomipramine. They may serve as adjuncts, but rarely replace prescription meds for moderate-to-severe OCD.
Comments (9)
Anderson Miller
31 Aug, 2026Look, I get it. You’re tired. You’ve been white-knuckling your way through exposure exercises for months and the brain just won’t shut up. But here’s the thing nobody tells you at the pharmacy counter: patience is literally the active ingredient in these meds. It’s not a bug, it’s a feature of how serotonin reuptake inhibition actually rewires neural pathways over time. If you quit because week two felt like hell on earth, you’re essentially quitting before the medicine even had a chance to bind properly to those transporters. Think of it like building muscle; you don’t lift heavy weights once and expect biceps. You have to endure the micro-tears first. The article nails the dosing reality-standard depression doses are basically homeopathic for OCD. Push for that higher range if your prescriber allows it. And yeah, the side effects suck, but transient nausea beats permanent mental anguish any day. Stick with it. The quiet is worth the noise.
kishhore kumar
1 Sep, 2026this is super helpful!! i was confused about why my dose seemed so low compared to what others said... now i understand the titration process better :)
Marshall Stephens
2 Sep, 2026I appreciate the balanced view here. Too often people demonize Clomipramine solely based on side effect profiles without acknowledging its efficacy in treatment-resistant cases. It’s important to remember that individual biochemistry varies wildly, and what works for one person might be ineffective or intolerable for another. The key takeaway seems to be communication with your provider rather than self-adjusting doses based on internet forums. That said, the emphasis on ERP therapy alongside medication is crucial; pills alone rarely resolve the behavioral loops entirely.
Aaron Gragg
2 Sep, 2026From a pharmacokinetic standpoint, the distinction between SSRIs and tricyclics regarding anticholinergic burden cannot be overstated. While SSRIs offer a cleaner receptor affinity profile primarily targeting the serotonin transporter (SERT), Clomipramine’s non-selective antagonism at muscarinic, histaminic, and adrenergic receptors necessitates rigorous cardiac monitoring due to potential QTc prolongation. Furthermore, the therapeutic window for OCD management is significantly wider than for major depressive disorder, requiring careful titration to avoid serotonergic toxicity while achieving sufficient synaptic concentration. Patients must also consider the implications of long-term adherence, particularly concerning metabolic parameters when utilizing agents with significant weight gain propensities. The integration of Exposure and Response Prevention remains the cornerstone of evidence-based practice, as neuroplasticity induced by cognitive-behavioral interventions complements the neurochemical modulation provided by pharmacotherapy. Without this synergistic approach, relapse rates upon discontinuation remain prohibitively high regardless of initial symptomatic remission achieved via monotherapy.
Curtis Surpless
2 Sep, 2026contrarian take: the "broken record" metaphor is lazy journalism. ocd isn't just looping thoughts it's a complex failure of error detection systems in the orbitofrontal cortex. also ssri vs clomipramine is false dichotomy augmentation strategies with glutamatergic agents show promise too. stop oversimplifying neuroscience for mass consumption.
Eryn Manchego
4 Sep, 2026oh wow this really hits home!! 🌈 the part about giving up too soon is so real. i almost quit prozac because i felt weird for two weeks but my therapist made me wait it out and now?? total game changer. the fog lifted. keep pushing friends 💪✨
Crystal Torres
5 Sep, 2026The timeline provided aligns well with clinical observations. However, it is imperative to note that individual responses can vary significantly based on genetic polymorphisms affecting drug metabolism enzymes such as CYP2D6. Therefore, close monitoring during the initial phase is essential to mitigate adverse events effectively.
Patrick van der Velde
6 Sep, 2026It is frankly embarrassing that we still need articles explaining basic psychiatric pharmacology to adults who presumably possess the cognitive capacity to read a prescription label. The reliance on SSRIs as a panacea reflects a broader societal laziness in addressing root causes rather than merely suppressing symptoms. One wonders if the pharmaceutical industry’s influence has skewed public perception away from more holistic, albeit less profitable, interventions. Nevertheless, if one must resort to chemical sedation, one ought to do so with intellectual rigor rather than blind faith.
Vivek Chaturvedi
8 Sep, 2026people complain about side effects but ignore the suffering of untreated ocd. moral obligation to seek help exists. stop whining about dry mouth when your life is controlled by rituals.